

Meniscus Surgery: Meniscectomy, Meniscus Repair and Transplantation
Summary: Surgery is not necessary for all meniscus injuries, but it may be considered if conservative measures fail. This article reviews arthroscopic knee procedures that have made meniscus surgery less intrusive than in the past, with shorter recovery times. It stresses that the decision to have surgery depends on many factors and should be made in close consultation with an orthopedic specialist who can evaluate the risks and benefits.

Do you need meniscus surgery? Signs and indications
Not all meniscus tears require surgery. The need for meniscus surgery depends on many factors, including the tear’s location, size, and whether it resulted from an acute trauma or from degeneration. Large, traumatic tears accompanied by mechanical symptoms like knee clicking, catching, buckling or locking are the most likely to benefit from surgery.
Other, patient-specific factors include the amount of knee pain involved, a person’s age, and the type of sports or level of physical activity they commonly perform.
Types of meniscus surgery
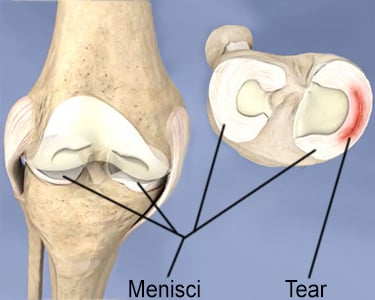
The two most common procedures are meniscus repair and meniscectomy. Meniscus transplant surgeries are also performed but are reserved for select cases. The appropriate surgical option for each person depends mostly on the specific location, size and morphology of the meniscus tear, as well as the age of the patient. One factor that plays a key role as to the choice between meniscus repair and meniscectomy is whether a meniscal tear or other damage is in the “red zone” or the “white zone” of the meniscus. The vascular anatomy of these two portions of the meniscus was first mapped by HSS researchers Steven Arnoczky, DVM, and Russell Warren, MD, in a landmark 1982 study. Their findings remain foundational to how surgeons decide between meniscus repair and meniscectomy today.
Meniscal red zone
The periphery of the meniscus is called the “red zone” because it receives blood flow. Tears in the red zone have a chance to heal following a repair, so a repair surgery is more likely performed for tears in the red zone. But the red zone composes only about 25% of the meniscus.
Meniscal white zone
The other 75% of the meniscus is called the “white zone” because it does not receive blood flow. A repair surgery to a tear in this area is more likely to fail, so a partial meniscectomy is often performed for “white zone” meniscal tears.
What is meniscus repair surgery? Techniques and approach
This is a procedure in which sutures are placed in the meniscus to fix the tear. There are many ways to perform a meniscus repair. The particular surgical technique used largely depends on the size and location of the tear.
The surgery begins with a knee arthroscopy to examine the meniscus and assess the meniscus tear. There are special suture implants that can be placed through the meniscus tear to allow repair of the meniscus. These implants do not require the surgeon to make additional incisions. For large meniscus tears, the surgeon often must make an additional incision to allow for passing of the sutures and tying knots for a more secure repair. These partial open techniques often allow for a more robust repair for larger meniscus tears than would arthroscopic techniques alone.
Video: Meniscal repair animation
What is a meniscectomy?
Meniscectomy, also commonly referred to as a partial meniscectomy, is a debridement (or “trimming”) of the meniscus. In this procedure, the torn areas of the meniscus are cut and removed using arthroscopic surgical tools, while the healthy areas of the meniscus are preserved. Meniscal debridement is often performed arthroscopically, involving minimally invasive incisions rather than open surgery.
The goal of a meniscectomy is to remove any unstable portions of the meniscus that are causing symptoms, but which may not be adequately treated with a repair. At the same time, it is important to minimize the amount of meniscus removed in order to preserve as much of this important shock absorber of the knee as possible.
Video: Meniscal trimming (partial meniscectomy)
Meniscus transplant surgery
The meniscus acts as a shock absorber for the knee, protecting its cartilage to prevent the progression of arthritis. When a person sustains an injury to the meniscus that leaves little or no viable meniscus tissue intact, they will have a much higher risk of developing knee arthritis and may benefit from a meniscus transplant. Young patients who have not developed arthritis but have severe damage to the meniscus are ideal candidates for meniscus transplant surgery. This surgery removes any remnant of meniscus tissue and then obtains an appropriately sized meniscus from a cadaver tissue bank, which is then placed in the knee. The donor tissue is repaired and sutured into place to allow the transplanted tissue to incorporate with the rest of the knee.
Meniscus surgery in conjunction with osteotomy for knee alignment
Oftentimes, there are underlying anatomic factors which may have contributed to extensive loss of meniscus tissue necessitating a meniscus transplant. A person who has a bowleg or knock knee deformity, for example, continually puts asymmetrical force on one side of their knee.
In these situations, it is important to correct the underlying deformity to maximize the longevity and success of the meniscus transplant. There are also situations where a patient may have relatively normal anatomy, but there are still opportunities to improve their knee alignment and reduce the stress on remaining meniscus tissue or a newly transplanted meniscus. These corrective procedures are known as osteotomies and involve cutting and realigning the bones above (femur) and/or below (tibia) the knee.
Orthobiologics in meniscus surgery
Regenerative Medicine is being increasingly incorporated as adjuncts during orthopedic knee surgery, including meniscus repair. Because large portions of the meniscus receive little direct blood supply, torn tissue in those areas have a limited ability to heal on their own after surgical suturing. Biologic agents used during surgery aim to compensate for this by delivering healing signals directly to the repair site.
The most established options used in clinical practice include autologous fibrin clot and platelet-rich plasma (PRP), both of which are made from the patient’s own blood and concentrate growth factors that stimulate tissue repair and attract healing cells. A related technique called marrow venting uses small puncture holes in the knee's intercondylar notch to introduce bone marrow elements into the joint. This recreates a biologically favorable environment that surgeons have long observed in cases where a meniscal repair is performed in conjunction with an ACL reconstruction. Collagen matrix wrapping combined with a bone marrow aspirate injection has also shown durable results in clinical follow-up.
Emerging biologic augmentation
Cell-based therapies and advanced scaffold materials show early promise in research settings, and this remains one of the most active areas in orthopedic science. None of the augmentation strategies described here are currently FDA-approved specifically for meniscal repair. Their use reflects evolving clinical judgment guided by a growing body of evidence.
Hospital stay after meniscus surgery
Most meniscus surgeries can be performed on an outpatient basis, meaning the patient goes home the same day as surgery. Occasionally the patient may stay one night in the hospital if they have additional surgeries that require closer observation.
Meniscus surgery recovery times
Recovery timelines vary significantly depending on which surgical procedure you have.
Meniscectomy recovery time
The recovery time from meniscectomy is typically faster than the recovery time from meniscus repair.
- Depending on the location of the tear, patients can usually put full weight on the leg right away.
- Occasionally the patient may need to use crutches for the first week.
- Most patients start resuming their normal sports activities 4 to 8 weeks after surgery depending on their preferred sports and activities.
Meniscus repair recovery time
Meniscus repair recovery time is typically 6 to 9 months depending on the activities of the patient. Competitive athletes may need up to nine months to return to play.
- Depending on the location of the tear, patients can usually put full weight on the leg right away.
- Occasionally the patient may need to use crutches for the first week.
- Most patients start resuming their normal sports activities 4 to 8 weeks after surgery depending on their preferred sports and activities.
Meniscus transplant surgery recovery time
The recovery process for a meniscus transplant requires an initial period of non-weight-bearing and then progression through physical therapy. It often takes 6 to 9 months to return to full activity, and most surgeons recommend not playing high-impact sports following a meniscus transplant surgery.
How soon can I drive after meniscus surgery?
Driving after meniscus surgery depends on which leg is treated. Following a meniscectomy, people can typically drive as soon as they are off any narcotic pain medications (typically one to three days). Following a meniscus repair surgery, most people can return to driving 2 to 3 weeks after surgery for a right sided surgery and 1 to 2 weeks following a left knee surgery.
What will happen if I don’t have meniscus surgery?
Many meniscus tears can be treated without surgery. Conservative options include physical therapy and corticosteroid injections.
In patients with degenerative meniscal tears and existing knee arthritis, research has shown physical therapy can produce comparable improvements in pain and function to meniscectomy. In an MRI-based study, patients who underwent meniscectomy showed greater short-term changes in joint structure – including increased cartilage damage and joint inflammation – in the 18 months following surgery compared to those who received physical therapy, though both groups improved clinically and the long-term significance of these imaging findings remains unclear.
Surgery is indicated for patients with persistent pain and mechanical symptoms of catching and locking that do not respond to conservative management such as physical therapy, NSAIDs, and injections. In these cases, delaying surgery can cause continued pain and limitations in daily activities. This can also result in further tearing and/or degeneration of the meniscus which may increase the risk of progressive arthritis. Additionally, certain tears which could have been repaired may no longer be repairable if not addressed in a timely fashion.
Risks and complications of meniscus surgery
Complications of arthroscopic knee surgery are rare, but any surgery comes with risks such as postsurgical blood clots, infections or damage to nerves or other tissues. The key benefits of meniscus surgery include resolution of pain and mechanical symptoms allowing return to activities without restrictions. Additional benefits include postponing or averting knee arthritis later in life and increasing knee stability.
Meniscus surgery success rates and outcomes
Success rates vary depending on both the type, location and severity of the tear, and which surgery is used to treat it. One study published in 2022 reported a greater than 80% success rate for meniscal repair five years after surgery. For example, greater outcomes were seen among repairs of lateral meniscus tears than medial tears. In a survey of HSS meniscectomy patients, 95% of respondents reported improvement within 12 months. In addition, research published independently of HSS found that 90% meniscectomy patients would recommend HSS compared to that of a national average of 70%. Learn more below.
Why choose HSS for meniscectomy?
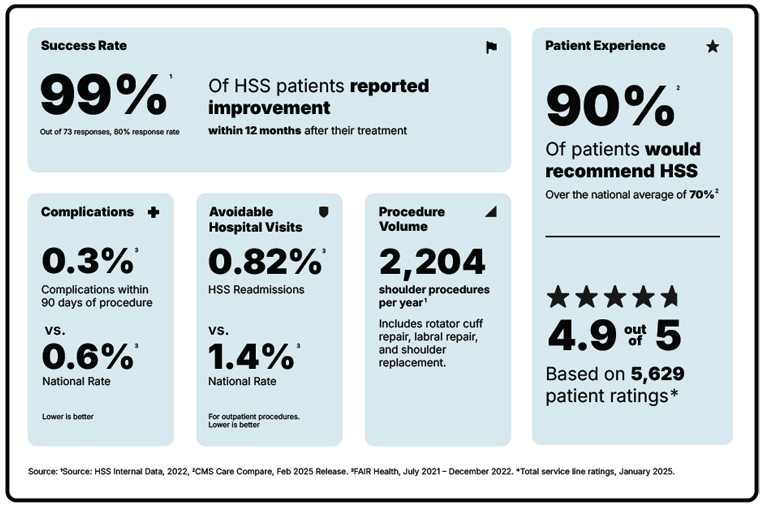
Meniscectomy is a surgery focused on reducing pain and getting you back to the activities you love. But not all hospitals achieve the same results. Some are more reliable than others. With the help of the HSS Hospital Reliability Scorecard, you can make sure you're asking the critical questions to find the hospital that's right for you. Understanding these data points will help you make the best decision for your care: See hospital reliability data
Key takeaways
- Not every meniscus tear requires surgery. Surgery may be considered for persistent pain or mechanical symptoms, especially catching or locking, that do not improve with physical therapy, medication or injections.
- The main surgical options are meniscus repair, which sutures the torn tissue; partial meniscectomy, which trims unstable tissue; and, less commonly, transplantation of a donor meniscus.
- Blood supply influences whether a tear can heal after repair. Tears in the vascular red zone are more repairable, while white-zone tears are more often treated with partial meniscectomy.
- Meniscus repair preserves the injured tissue whenever feasible. Partial meniscectomy removes symptomatic, unstable tissue that cannot be repaired while retaining as much healthy meniscus as possible.
- Meniscus transplant may benefit younger patients with extensive tissue loss but no arthritis. Corrective osteotomy may accompany transplantation when knee alignment places excessive stress on the meniscus.
- Orthobiologic treatments such as fibrin clot, platelet-rich plasma and marrow venting may support meniscus healing. However, these augmentation strategies are not FDA-approved specifically for meniscal repair.
- Recovery depends on the procedure. Meniscus repair and transplantation typically require 6 to 9 months, while recovery from partial meniscectomy is faster, with sports often resumed within 4 to 8 weeks.
Dr. Tony Wanich is an Orthopedic Surgeon at the HSS Sports Medicine Institute specializing in the management of injuries to the shoulder, knee, and elbow. He is a Team Physician for the New York Mets and the Red Bull New York Major League Soccer team, and has been recognized as one of New York’s top doctors in Castle Connolly since 2016, New York Magazine and NJ Monthly.


Authors

Explore Related Patient Stories
View All Patient Stories
Jillian Pulicicchio
Seattle, WA
Meniscus Tear (Torn Meniscus)

James Anagnostopoulos
Sunny Isles Beach, FL
Meniscus Tear (Torn Meniscus)

Sarah Baglio
Bronx, NY
Meniscus Tear (Torn Meniscus)

April McConnell
New York, NY
Meniscus Tear (Torn Meniscus)

Vlada Yaneva
Sofia, Bulgaria
Meniscus Tear (Torn Meniscus)

Scott Meyer
Mount Kisco, NY
Meniscus Tear (Torn Meniscus)

Elias Kishelev
South Orange, NJ
Meniscus Tear (Torn Meniscus)

Bridget Moschetti
Haverstraw, NY
Meniscus Tear (Torn Meniscus)

Peter Hurley
New York, NY
Meniscus Tear (Torn Meniscus)

Mark Klapper
Rye Brook, NY
Meniscus Tear (Torn Meniscus)

Joanne Fundaro
Brooklyn, NY
Meniscus Tear (Torn Meniscus)

Rhona Chambers
New York, NY
Meniscus Tear (Torn Meniscus)

Natalia Oblonsky
New York, NY
Meniscus Tear (Torn Meniscus)

Daniel O'Brien
Greenwich, CT
Meniscus Tear (Torn Meniscus)
Edward Martin
Brooklyn, NY
Meniscus Tear (Torn Meniscus)

Kevin Sorce
Stockholm, NJ
Meniscus Tear (Torn Meniscus)

Barbara Gorman
New York, NY
Meniscus Tear (Torn Meniscus)

Jim Bosche
New York, NY
Meniscus Tear (Torn Meniscus)

Casey Garlasco
Paramus, NJ
Meniscus Tear (Torn Meniscus)

Patti Freda
Greenwich, CT
Meniscus Tear (Torn Meniscus)
References
- Arnoczky SP, Warren RF. Microvasculature of the human meniscus. Am J Sports Med. 1982 Mar-Apr;10(2):90-5. doi: 10.1177/036354658201000205. PMID: 7081532. https://pubmed.ncbi.nlm.nih.gov/7081532/
- Bansal S, Floyd ER, A Kowalski M, Aikman E, Elrod P, Burkey K, Chahla J, LaPrade RF, Maher SA, Robinson JL, Patel JM. Meniscal repair: The current state and recent advances in augmentation. J Orthop Res. 2021 Jul;39(7):1368-1382. doi: 10.1002/jor.25021. Epub 2021 Mar 19. PMID: 33751642; PMCID: PMC8249336. https://pubmed.ncbi.nlm.nih.gov/33751642/
- Collins JE, Shrestha S, Losina E, Marx RG, Guermazi A, Jarraya M, Jones MH, Levy BA, Mandl LA, Williams EE, Wright RW, Spindler KP, Katz JN; METEOR Investigator Group. Five-Year Structural Changes in the Knee Among Patients With Meniscal Tear and Osteoarthritis: Data From a Randomized Controlled Trial of Arthroscopic Partial Meniscectomy Versus Physical Therapy. Arthritis Rheumatol. 2022 Aug;74(8):1333-1342. doi: 10.1002/art.42105. Epub 2022 Jun 28. PMID: 35245416; PMCID: PMC9339455. https://pubmed.ncbi.nlm.nih.gov/35245416/
- Hutchinson ID, Rodeo SA. The Current Role of Biologics for Meniscus Injury and Treatment. Curr Rev Musculoskelet Med. 2022 Dec;15(6):456-464. doi: 10.1007/s12178-022-09778-z. Epub 2022 Jul 26. PMID: 35881326; PMCID: PMC9789233. https://pubmed.ncbi.nlm.nih.gov/35881326/
- Katz JN, Collins JE, Jones M, Spindler KP, Marx RG, Mandl LA, Levy BA, Wright R, Jarraya M, Guermazi A, MacFarlane LA, Losina E, Chang Y. Association Between Structural Change Over Eighteen Months and Subsequent Symptom Change in Middle-Aged Patients Treated for Meniscal Tear. Arthritis Care Res (Hoboken). 2023 Feb;75(2):340-347. doi: 10.1002/acr.24796. Epub 2022 Oct 21. PMID: 34606692; PMCID: PMC8977396. https://pubmed.ncbi.nlm.nih.gov/34606692/
- Nepple JJ, Block AM, Eisenberg MT, Palumbo NE, Wright RW. Meniscal Repair Outcomes at Greater Than 5 Years: A Systematic Review and Meta-Analysis. J Bone Joint Surg Am. 2022 Jul 20;104(14):1311-1320. doi: 10.2106/JBJS.21.01303. Epub 2022 Apr 19. PMID: 35856932. https://pubmed.ncbi.nlm.nih.gov/35856932/
- Su L, Garcia-Mansilla I, Kelley B, Arshi A, Fabricant PD, Sherman SL, Jones KJ. Clinical Outcomes of Meniscal Allograft Transplantation With Respect to the Minimal Clinically Important Difference. Am J Sports Med. 2022 Oct;50(12):3440-3446. doi: 10.1177/03635465211036116. Epub 2021 Sep 8. PMID: 34495780. https://pubmed.ncbi.nlm.nih.gov/34495780/
- Taylor SA, Rodeo SA. Augmentation techniques for isolated meniscal tears. Curr Rev Musculoskelet Med. 2013 Jun;6(2):95-101. doi: 10.1007/s12178-013-9165-z. PMID: 23512636; PMCID: PMC3702772. https://pubmed.ncbi.nlm.nih.gov/23512636/
- Wanich T, Zelken J, Rodeo S, Bonassar L, Warren R. P131 Functional tissue engineering of a meniscal substitute. Osteoarthritis Cartilage. 2007;15. doi:10.1016/S1063-4584(07)61486-1.